The Refill That Feels Routine: Butalbital Stewardship in U.S. Headache Care
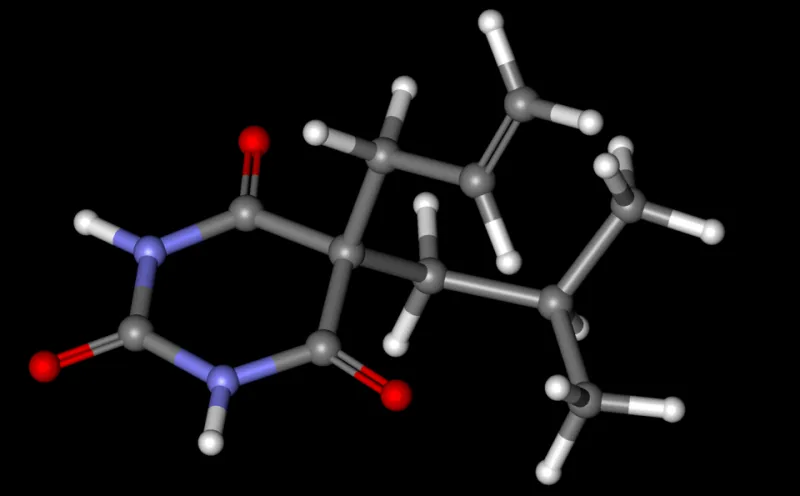
Photo: MarinaVladivostok, CC0, via Wikimedia Commons
Butalbital combination products occupy an odd place in U.S. outpatient medicine. They are prescribed for headache, dispensed like ordinary symptom relief, and often discussed in the language of convenience rather than controlled-substance risk. A patient may know the product by a brand name or by its reputation for stopping a difficult headache, not by the fact that the formulation contains a barbiturate. That gap between perception and pharmacology is the starting point for any serious stewardship effort.
The clinical ethics question is not whether butalbital should disappear from practice. It is whether clinicians and policymakers can see hidden barbiturate exposure clearly enough to counsel, monitor, and taper when appropriate, while preserving access for patients whose episodic use remains reasonable. Alarmism is not a safety strategy. Neither is routine refilling without review.
Why the Headache Frame Obscures the Risk
Butalbital is usually encountered in combination with acetaminophen, aspirin, and caffeine. The familiar package can make the product feel like a multi-ingredient headache remedy rather than a sedative-hypnotic exposure. Patients may focus on the analgesic component and underestimate the barbiturate component. Clinicians may inherit the framing from a prior prescriber and continue a refill because the visit is about headache control, not substance safety.
That framing matters because butalbital carries dependence potential, tolerance, and withdrawal risk. Chronic use can contribute to medication-overuse headache, a clinical trap in which escalating refills appear to treat the problem while sustaining it. Overdose risk rises when butalbital is combined with opioids, benzodiazepines, alcohol, or other central nervous system depressants. These are not exotic scenarios; they are common co-exposures in U.S. ambulatory care.
The ethical obligation is to communicate this without converting every headache patient into a suspect. A harm-reduction lens asks what the patient needs to know, what the prescriber needs to document, and what the system needs to detect. It does not require moralizing about refill requests.
The Prescribing Pattern That Deserves an Audit
A practical audit begins with quantity and cadence. How many dosage units is the patient receiving per month? Is the prescription written as needed but refilled on a fixed schedule? Are refills arriving through multiple pharmacies, telehealth channels, or urgent care visits? Does the patient receive butalbital alongside a benzodiazepine, opioid, muscle relaxant, or sleep aid? These questions are more useful than a single yes-or-no judgment about whether the drug is appropriate.
State prescription drug monitoring programs can reveal overlapping controlled-substance fills, but butalbital combination products are not uniformly treated across jurisdictions. Federal and state scheduling varies by formulation, and pharmacy practice may differ. Policy readers should resist assuming that a PDMP check is a complete answer. It is one data source, not a diagnosis of misuse.
The refill cascade is especially important in headache care because the drug is often prescribed episodically and then renewed by habit. A patient who once used a small quantity for occasional tension headache may drift into weekly use without a formal decision ever being made. The audit should ask when the prescription changed from episodic rescue to routine maintenance, and whether anyone documented that transition.
Counseling Gaps and Ethical Communication
Counseling should be specific, plain, and nonjudgmental. Patients should understand that the product contains a barbiturate, that daily use can worsen headache frequency, that abrupt cessation after prolonged use can precipitate withdrawal, and that combining it with alcohol or sedatives increases overdose risk. The message should not be that the patient has done something wrong. It should be that the medication has risks that deserve a plan.
Clinicians also need language for the patient who is afraid of losing relief. A harm-reduction approach can acknowledge that butalbital may have helped in the short term while explaining why frequent use is a poor long-term strategy. The goal is shared decision-making about alternatives, not a lecture. Migraine prophylaxis, non-barbiturate acute treatments, trigger management, and referral to neurology or pain specialists may all be relevant depending on the clinical picture.
When dependence is suspected, abrupt discontinuation is not a casual office instruction. Barbiturate withdrawal can be medically serious. Tapering should be individualized, documented, and coordinated, especially for patients with long-term use or co-occurring sedative exposure. The ethical failure is not the presence of a taper; it is a taper imposed without explanation, support, or follow-up.
A Harm-Reduction Checklist for Busy Practice
- Identify every patient receiving a butalbital combination product and document the indication, quantity, and refill history.
- Quantify monthly exposure rather than relying on the phrase as needed.
- Screen for alcohol, opioid, benzodiazepine, and other sedative use at each renewal.
- Ask about headache frequency and medication-overuse patterns before extending a refill.
- Counsel on dependence, withdrawal, and overdose risk in plain language.
- Offer non-barbiturate alternatives and prophylaxis when clinically appropriate.
- Use a structured taper for chronic use, with follow-up and withdrawal precautions.
- Coordinate with pharmacists when multiple prescribers or pharmacies appear in the record.
- Document the rationale for continuation, taper, or discontinuation.
Policy Levers Without Punitive Framing
Policy can support this work without turning headache patients into collateral damage. Payers and health systems can build renewal prompts that ask about quantity and co-prescribed sedatives. Telehealth standards can require a documented medication history before butalbital is refilled. Pharmacists can be empowered to flag escalating cadence and duplicate therapy. None of these levers requires a punitive tone; each can be framed as medication safety.
The deeper policy question is surveillance. If butalbital exposure is hidden by familiar branding and routine refills, then U.S. drug-safety systems will continue to undercount it. Better outpatient monitoring, clearer counseling standards, and consistent documentation would help clinicians see the risk before an overdose or withdrawal crisis makes it visible. That is the harm-reduction case for butalbital stewardship: not fewer headaches treated, but fewer barbiturate exposures left unexamined.